These developments, along with broader public interest, may be contributing to FDAs consideration of whether to permit peptide use in compounding
Disclosure of interest: Daniel Ullrich: nothing to disclose, Heike Heuer: nothing to disclose, Steffen Mayerl: nothing to disclose, Dagmar Fhrer: nothing to disclose, Christoph Kleinschnitz: nothing to disclose, Friederike Langhauser: nothing to disclose E-Posters - ACUTE ISCHEMIC STROKE MANAGEMENT 01.00 - ACUTE ISCHEMIC STROKE MANAGEMENT - 01.04 - THROMBOLYSIS P2110 - ESOC25-1904 THROMBOLYSIS UTILIZATION AND OUTCOMES IN A PERIPHERAL CENTRAL HOSPITAL COHORT OF SUPRATENTORIAL ISCHEMIC STROKE Jussi Sipil 1,2 , Juha Pkknen 1 , Ayla Mehdiyeva 1,2 , Matti Heikkinen 1,2 , Mohamed Hassan 1,2 , Liisu Balk 1 , Minna Johanna Willman 1 , Albina Kettunen 1 , Anna Saukkonen 1 , Jari Toivanen 1 1 North Karelia Central Hospital, Joensuu, Finland, 2 University of Eastern Finland, Kuopio, Finland Background and Aims: IVT appears underutilised

Injection Technique Best Practices Proper subcutaneous injection technique for cagrilintide follows these steps: Preparation Allow refrigerated peptide to reach room temperature (15-30 minutes) Hygiene Wash hands thoroughly and clean injection site with alcohol swab Pinch technique Gently pinch skin to create a fold of subcutaneous tissue Insertion angle Insert needle at 45-90 degree angle depending on subcutaneous fat thickness Injection Depress plunger slowly and steadily over 5-10 seconds Withdrawal Wait 5 seconds after full depression, then withdraw needle smoothly Pressure Apply gentle pressure with clean gauze if needed (do not rub) For researchers working with peptide administration protocols, these techniques ensure consistent delivery and reproducible results
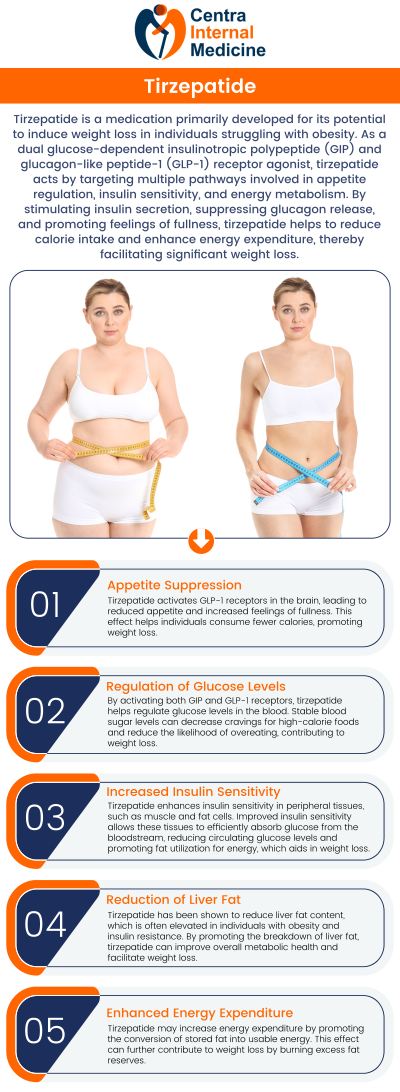
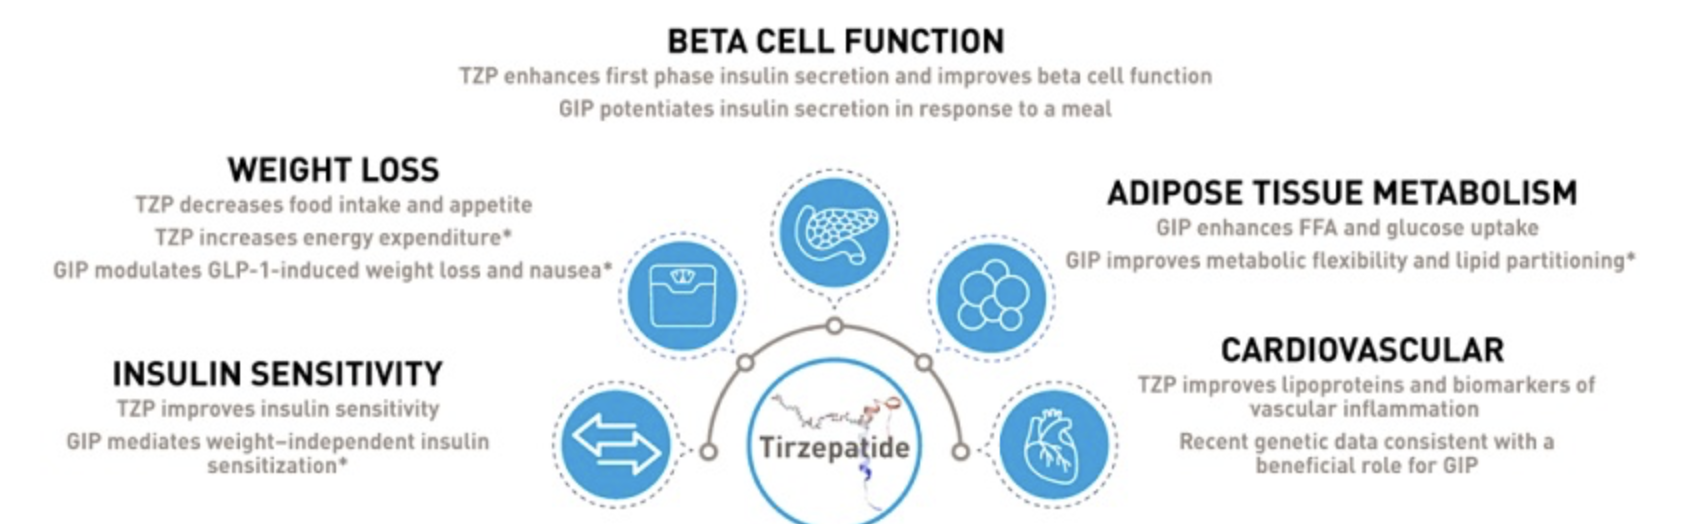
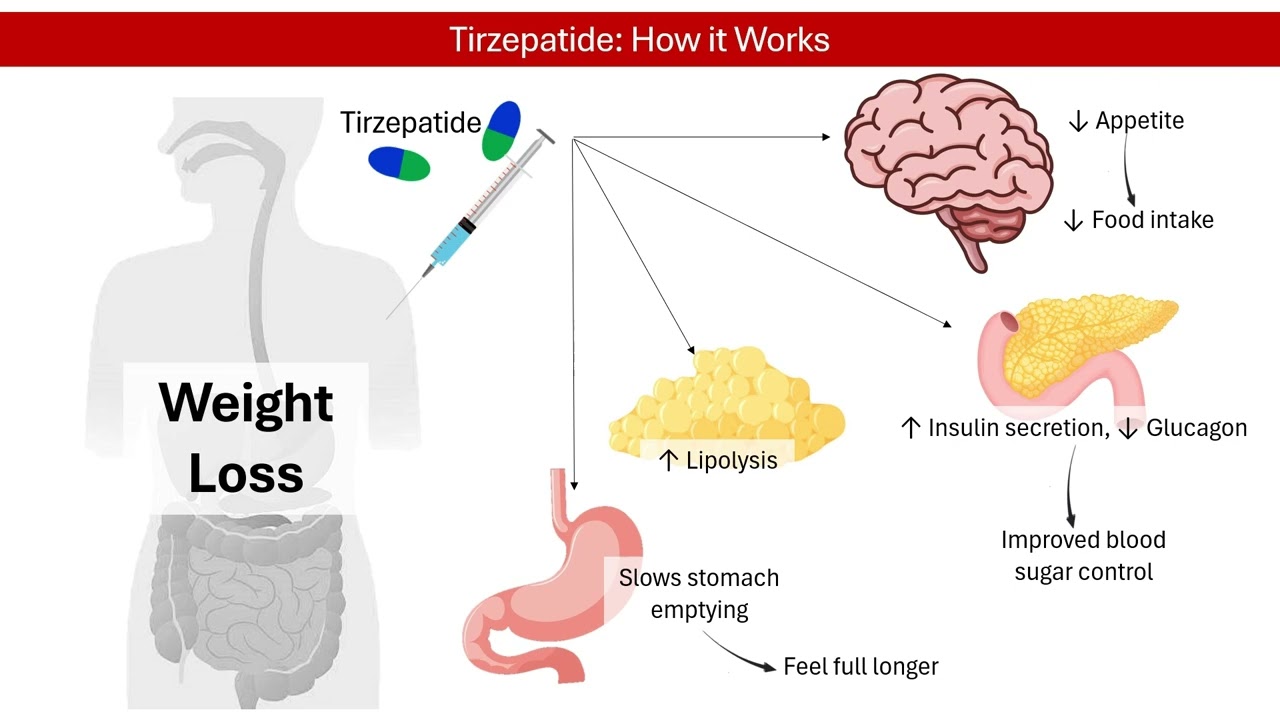
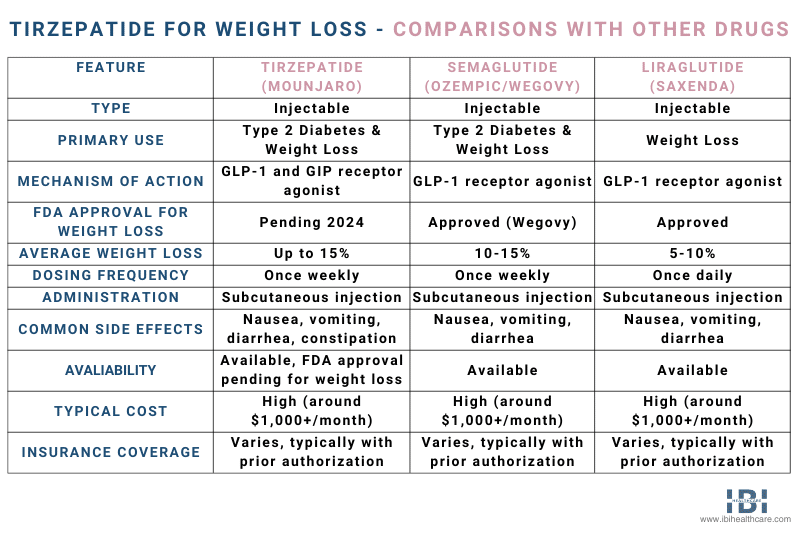
Tirzepatide doses range from 2.5 mg to 15 mg per week, roughly 6 to 10 times higher in milligram terms